
CPT code 91200 is a code that gets rejected more often than most practices are aware of and can result in lost revenue quickly. The CPT code for liver elastography using mechanically induced shear waves (i.e. FibroScan) without real-time B-mode ultrasound imaging is 91200 (CPT code).
Claims payment for medical testing is typically based on three criteria: complete and accurate documentation of the testing, correct application of modifiers, if necessary, and an appropriate diagnosis codes for the testing performed. This article covers the complete CPT code 91200 medical billing for transient elastography testing of the liver.
CPT Code 91200 is a diagnostic gastroenterology procedure that the AMA groups with the other tests. The CPT code 91200 refers to a liver transient elastography test. This test uses a probe to send a mechanical pulse to the liver and then measure and determine the speed of the shear wave.
A device is used in the clinic by placing a probe on the right lower rib cage of a patient. Low frequency pulses are rapidly fired through the probe and the time taken for each pulse to travel through the liver tissue is measured with sensors.
Values are expressed in kilopascals (kPa) or in m/s. Most recent ultrasound devices for liver fibrosis measurement also calculate a Controlled Attenuation Parameter (CAP) value during the measurement and display it immediately. The liver fat content can thus be estimated during the same session.
Billers mix these three up all the time, and it’s easy to see why. A FibroScan CPT code claim can look a lot like a general abdominal ultrasound on paper, but the services are different.
Billing Parameter | CPT Code 91200 | CPT Code 76981 | |
Official Name | Liver elastography, mechanically induced shear wave | Ultrasound, elastography parenchyma | Ultrasound, abdominal limited |
Imaging Component | No B-mode real-time imaging | Performed with real-time 2D ultrasound | Full B-mode diagnostic imaging |
Primary Clinical Use | Noninvasive assessment of diffuse liver stiffness | Stiffness evaluation within an ultrasound exam | Anatomic view of the liver, gallbladder, or ducts |
Equipment | FibroScan-type hardware (VCTE) | Diagnostic ultrasound with elastography software | Standard diagnostic B-scan ultrasound |
Don’t bundle these without a reason. The National Correct Coding Initiative (NCCI) has edits aimed squarely at this. If you ran a standard transient elastography test with no anatomical imaging, bill 91200 by itself. Falsely billing an abdominal ultrasound code is one of the fastest ways to have a claim denied.
CPT code 91200 billing is influenced by where the scan is performed and who owns the machine. The following CPT code 91200 billing information from two facts:
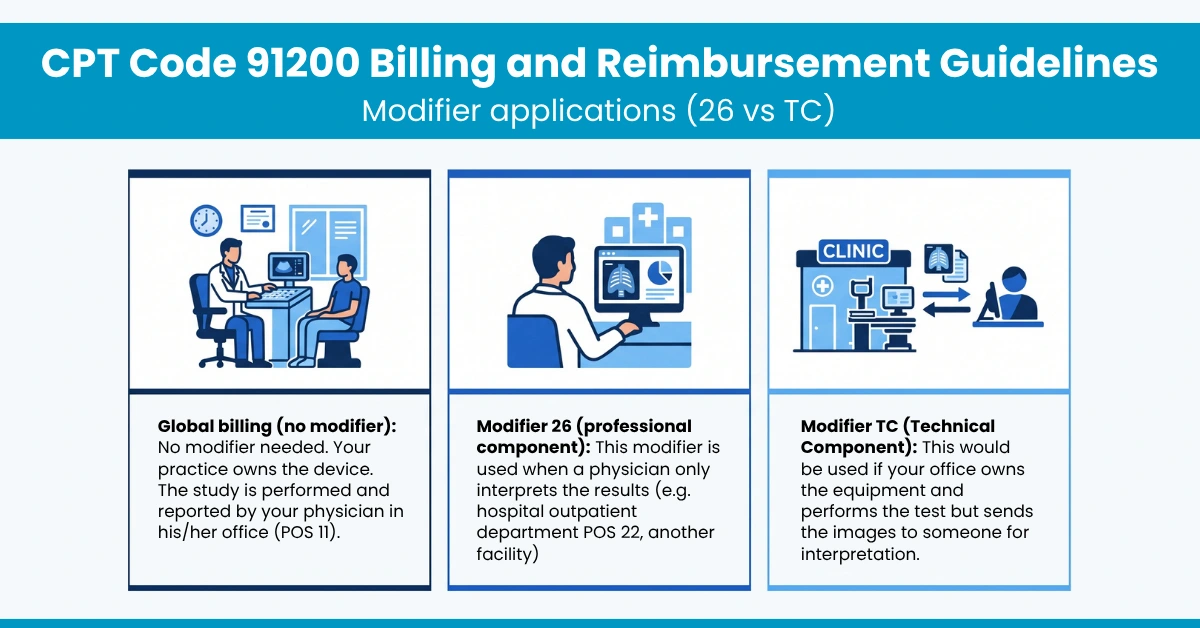
Medicare’s global payment for CPT code 91200 has been around $33.73, though geographic adjustments shift the final number. Check the current figure in the CMS Physician Fee Schedule before you budget around it. Commercial payers such as Aetna, Cigna, and UnitedHealthcare often pay more for this liver elastography CPT code, usually when prior authorization is in place.
If the physician also performs a separate E/M visit the same day, put Modifier 25 on the E/M code, and make sure the note actually supports a distinct service.
Clean CPT code 91200 coding starts with solid chart notes. Auditors look hard at CPT code 91200 documentation requirements before a payer releases funds. Each record should include:
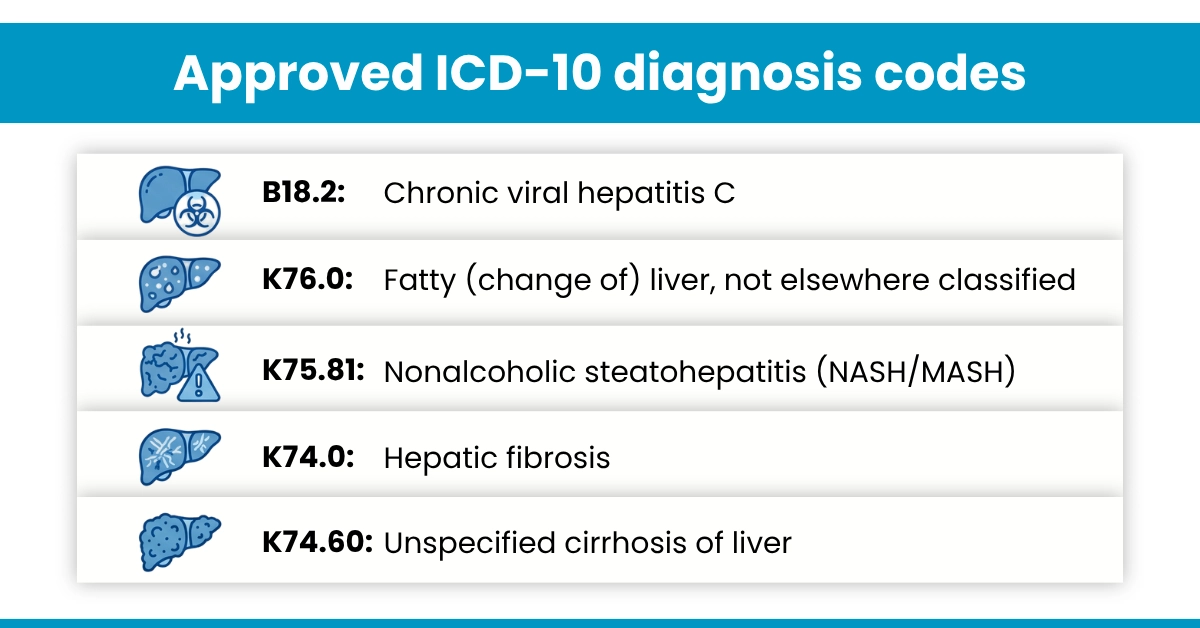
Pairing 91200 with a routine screening code is a fast route to rejection. The claim needs a diagnosis that establishes CPT code 91200 medical necessity:
Payer policies differ, so check each carrier’s coverage policy for accepted diagnoses.
CPT code 91200 transient elastography denials are caused by a few of the same problems. Addressing these early can help to keep your A/R in check.
Your best defense is a set of rules for the clearinghouse scrubbing that identifies missing modifiers, questionable ICD-10 code pairs, and missing authorizations before the claim is released from your office.
Add your own proof point here: a real denial pattern your coders have seen on 91200, or a before/after example with anonymized numbers. This is the single biggest thing that makes the page read as human and rank as original.
Coding shouldn’t pull your team away from patients. Our AAPC-certified coders handle revenue cycle management for GI practices, including denials, authorizations, and clean-claim follow-through, so revenue stops leaking.
Want to see where your clinic is losing money? Schedule a meeting for a free billing audit.
This guide is for educational and informational purposes only. Medical billing policies and coding guidelines change frequently. Always consult official AMA CPT manuals, CMS regulations, and specific payer policies
Traditional Medicare Part B usually doesn’t, as long as the diagnosis supports medical necessity under your MAC’s coverage rules. Medicare Advantage and commercial plans are a different story, and plenty of them want an authorization on file before the scan is scheduled. Check with each plan before the patient comes in.
Modifier 53 (discontinued procedure) is the usual choice when the scan is started and then has to stop, for example because the patient is uncomfortable or body habitus prevents valid readings. Document why you stopped and how many valid measurements you got. Some payers won’t pay for a scan that never reached 10 valid measurements, so look at their policy first. Facilities billing hospital outpatient claims typically use 73 or 74 instead.
Yes, the code isn’t limited by age. What matters is whether the payer sees medical necessity, so the chart should spell out the reason, such as monitoring metabolic-related liver disease, biliary atresia, or liver injury from a medication. Coverage for children varies quite a bit between plans.
Add Modifier 76 if the same physician repeats the scan, or Modifier 77 if a different physician does. That tells the payer the second scan wasn’t a duplicate submission. Expect scrutiny, since most payers allow one unit per day. A repeat caused by a technical problem on the first attempt is often not payable, so your notes need to show why the second scan was medically necessary.
CPT Code 91200 serves as the standardized medical code used to report liver transient elastography performed without real-time B-mode ultrasound imaging. Medical practices often experience claim denials or underpayment for transient elastography (commonly known as a FibroScan procedure) due to improper modifier usage, misaligned diagnosis codes, or unbundling errors. Understanding how to properly bill CPT Code 91200 ensures full compliance, optimal reimbursement, and a streamlined revenue cycle for gastroenterology and hepatology practices.
CPT Code 91200 is defined by the American Medical Association (AMA) as liver elastography, mechanically induced shear wave, without imaging. This diagnostic test evaluates liver stiffness noninvasively, helping clinicians assess hepatic fibrosis and cirrhosis without requiring an invasive liver biopsy.
During the clinical examination, a specialized probe is positioned against the patient’s right lower intercostal space. The device emits a low-frequency mechanical vibration (50 Hz) that generates a shear wave propagating through the liver tissue. Ultrasound sensors track the speed of this shear wave as it travels through the hepatic parenchyma.
Results are calculated and displayed in kilopascals (kPa), ranging typically from 1.5 kPa to 75 kPa. Modern elastography platforms also calculate a Controlled Attenuation Parameter (CAP) score, which measures ultrasound attenuation to quantify hepatic steatosis (fat accumulation) during the same diagnostic session.
Billing staff frequently confuse CPT Code 91200 with other diagnostic ultrasound codes. Selecting the wrong code can trigger National Correct Coding Initiative (NCCI) edits and lead to immediate claim rejections. The table below outlines the critical distinctions among these diagnostic codes:
| Billing Parameter | this billing code | CPT Code 76981 | CPT Code 76705 |
|---|---|---|---|
| Official Long Title | Liver elastography, mechanically induced shear wave | Ultrasound, elastography, parenchyma (e.g., organ) | Ultrasound, abdominal, real-time with image documentation; limited |
| Imaging Requirement | No real-time B-mode ultrasound imaging | Requires concurrent real-time 2D ultrasound visualization | Full anatomical diagnostic B-mode imaging |
| Primary Diagnostic Purpose | Noninvasive measurement of liver stiffness (fibrosis/steatosis) | Targeted parenchymal stiffness assessment within a broader ultrasound exam | Anatomical evaluation of liver, gallbladder, or biliary tree |
| Hardware Utilized | Vibration-Controlled Transient Elastography (VCTE / FibroScan) | Standard diagnostic ultrasound with elastography software module | Standard diagnostic B-scan ultrasound system |
Submitting a claim for abdominal ultrasound when only transient elastography was performed constitutes improper billing. Practices must ensure equipment capabilities and clinical intent dictate code selection.
Reimbursement for CPT Code 91200 depends heavily on the place of service (POS), equipment ownership, and correct modifier appendance. Payers recognize global, professional, and technical components for this diagnostic test.
If an Evaluation and Management (E/M) service is delivered on the exact same day as transient elastography, append Modifier 25 to the E/M code. Documentation must clearly show that the E/M service was significant, separately identifiable, and above and beyond the standard pre- and post-procedure care associated with this billing code.
Medicare Administrative Contractors (MACs) establish local coverage determinations (LCDs) governing reimbursement rates for transient elastography. Allowable amounts can be verified via the official CMS Physician Fee Schedule. Commercial insurance carriers, including Aetna, Cigna, and UnitedHealthcare, frequently require prior authorization and specific medical necessity criteria prior to approving this billing code reimbursement.
Also read: Explore our complete guide on Main Accounting Reports for Small Businesses.
To withstand post-payment payer audits, clinical documentation must thoroughly support medical necessity. Chart records for CPT Code 91200 must explicitly include the following elements:
Attaching non-covered or routine screening diagnosis codes to CPT Code 91200 claims results in automatic claim denials. High-probability ICD-10 codes supporting medical necessity include:
Avoiding common billing traps keeps accounts receivable (A/R) low and maintains constant practice cash flow. Key denial reasons for CPT Code 91200 include:
Traditional Medicare Part B generally does not require prior authorization for CPT Code 91200, provided an approved ICD-10 code demonstrating medical necessity is billed. However, Medicare Advantage plans and private commercial payers frequently enforce prior authorization requirements before coverage is granted.
Use Modifier 53 (discontinued procedure) if the physician elects to terminate the elastography scan due to patient discomfort or anatomical body habitus limitations. Documentation must describe the reason for discontinuation and report the number of successful measurements obtained.
Yes, pediatric practices can bill CPT Code 91200 when evaluating pediatric liver disorders, such as nonalcoholic fatty liver disease, biliary atresia, or drug-induced liver injury. Medical necessity guidelines established by the specific payer must be met.
If a repeat scan is clinically necessary on the same calendar date by the same practitioner, append Modifier 76 (repeat procedure by same physician). If conducted by a different practitioner, append Modifier 77. The medical record must clearly state the clinical necessity for repeating the diagnostic test.