
CPT code 95886 is the add-on code for a complete needle EMG on one extremity, billed the same day as a nerve conduction study. Neurology and physical medicine practices report it often, and it still gets denied or downcoded more than most codes in the EMG/NCS family.
Two problems cause most of it: A muscle count that lands one short of “complete,” and a nerve conduction code that’s missing or mismatched on the same claim. Here’s what CPT Code 95886 covers, how it differs from 95885 and 95887, which ICD-10 codes payers expect with it, and the exact documentation gap behind most denials.
CPT Code 95886 reports a complete needle EMG of one extremity, plus the related paraspinal muscles when tested. “Complete” has a specific meaning: the study has to cover five or more muscles, supplied by at least three different nerves, or map to four or more spinal levels.
During the test, a physician inserts a thin needle electrode into each muscle and records its electrical activity at rest and during contraction. The goal is to spot patterns that point to nerve or muscle disease; radiculopathy, neuropathy, and myopathy are the usual suspects.
CPT Code 95886 is an add-on code. It carries the standard add-on instruction to report it alongside a primary procedure code. That means it can never be the only code on a claim line; it has to ride along with a nerve conduction study performed the same day.
The three add-on EMG codes are separated by one thing: how many muscles get tested in that extremity, and where. Four or fewer muscles is 95885. Five or more, spread across three-plus nerves or four-plus spinal levels, is CPT code 95886. Muscles outside the extremities, face, jaw, trunk, fall under 95887.
| Code | Muscles tested | Nerve/level rule | Use case |
| +95885 | 4 or fewer per extremity | — | Limited extremity EMG, same-day NCS |
| +95886 | 5 or more per extremity | 3+ nerves or 4+ spinal levels | Complete extremity EMG, same-day NCS |
| +95887 | Non-extremity muscles | — | Cranial-nerve or axial muscles, same-day NCS |
This threshold comes from AMA’s own CPT coding conventions, and AAPC’s coding guidance confirms the same per-extremity counting rule most payers apply.
All three codes need a same-day nerve conduction study to be billable; none of them work standing alone. If no NCS happens that day, the visit gets coded with the standalone extremity EMG codes (95860-95864) instead, not with 95885 through 95887.
CPT Code 95886 only pays when it’s attached to a primary nerve conduction study code, specifically 95907 through 95913, chosen by how many individual nerve studies were run. Drop the NCS code, and CPT code 95886 has nothing to attach to.
A few billing rules trip practices up here:
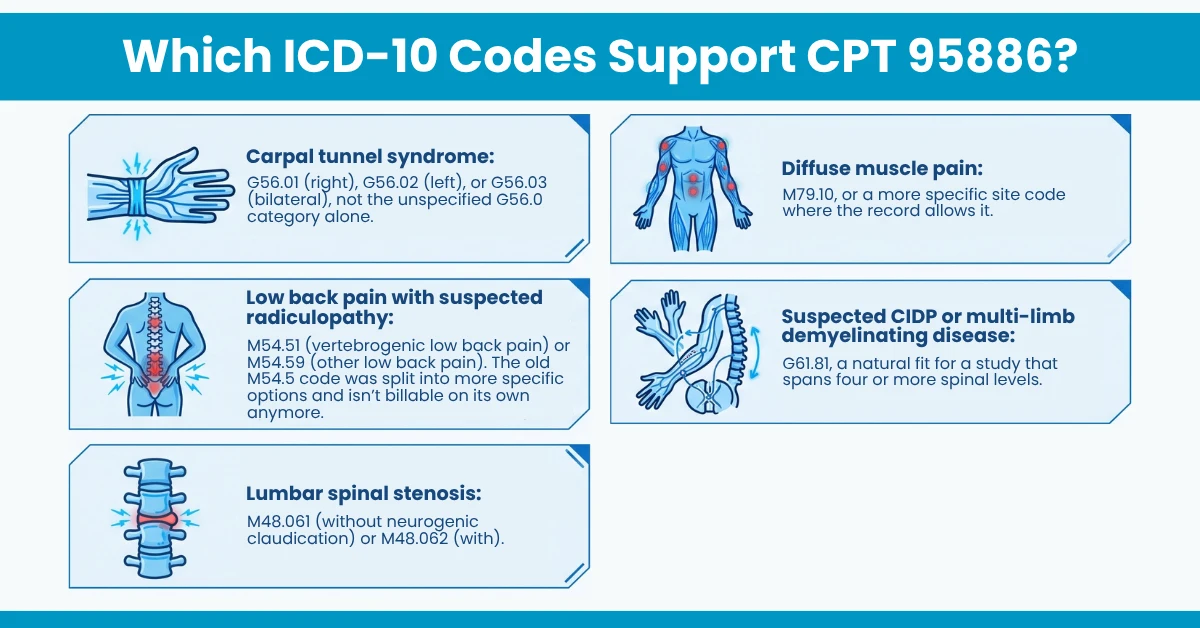
CPT Code 95886 needs a diagnosis code that points to a real neuromuscular or nerve workup. Pain alone rarely justifies a complete, multi-muscle EMG. A handful of ICD-10 codes cover most of the visits we see, and two of them changed in recent years:
Match the diagnosis to what the note actually documents. A payer that sees “myalgia” attached to a four-limb, twelve-muscle study is going to ask questions.
The single biggest reason CPT Code 95886 gets downcoded isn’t a missing code. It’s a muscle count that doesn’t reach five. State workers’-compensation fee-dispute records show this pattern over and over. A claim bills CPT code 95886, but the note only documents four muscles per extremity, which meets the bar for 95885, not CPT code 95886.
The fix is documentation, not billing. Every muscle tested needs to be named individually in the note, along with the nerve or spinal level it maps to. “Bilateral lower extremity EMG performed” doesn’t hold up on review. “Right and left tibialis anterior, gastrocnemius, gluteus medius, rectus femoris, and vastus lateralis, spanning the femoral, peroneal, and tibial nerves” does.
A few other checks worth running before the claim goes out:
Our Denial Management team reviews claims against exactly this checklist before resubmission, which is usually faster than waiting on an appeal.
CPT Code 95886 gets paid when three things line up: A same-day NCS code from the current 95907-95913 range, a muscle count that actually reaches five per extremity, and a diagnosis code that matches the note. Most denials trace back to one of those three, not to anything mysterious.
If your EMG/NCS claims have been coming back downcoded or denied, our Medical Billing Audit Services team will review a sample of recent claims and show you exactly where the pattern is breaking down; no cost, no obligation.
Coding and payer rules change often. Confirm current code sets and payer-specific requirements before filing a claim, this article is educational and isn’t compliance or legal advice.